Table of contents
A temporomandibular disorder (TMD, often called TMJ) affects women significantly more often than men. An analysis of population studies found that women face roughly twice the risk (odds ratio 2.24). Despite this, many women’s symptoms remain undiagnosed for years because TMD rarely presents as a clear “jaw problem.” Instead, it often manifests through seemingly unrelated symptoms such as headaches, neck tension, or ringing in the ears. In this article, you will learn how to recognize TMD in yourself, why women are particularly affected, how the examination works, and how it is treated.

Specialist in orthodontics. Owner of JUST KFO in Cologne, sought-after speaker and author who regularly appears in professional publications and media.
Full profile →Why are women more often affected by TMD?
The fact that women more often develop a temporomandibular disorder has several reasons that act together. A single trigger can rarely be identified – usually it is an interplay of physical and situational factors.
Hormonal influences
The female sex hormone estrogen affects the connective tissue and cartilage structures in the temporomandibular joint. Fluctuations during the menstrual cycle, pregnancy, or menopause can alter the joint’s resilience and encourage symptoms. Pain perception is also subject to hormonal influences, which may explain why symptoms appear more pronounced during certain life phases. A review article from 2024 concludes that estrogen plays an important role in the development of TMD-related pain.
Stress and nighttime teeth grinding
Persistent tension frequently leads to unconscious clenching, especially during the day. Nighttime grinding has many causes; stress is one of them. Both can overload the masticatory muscles and are considered a risk factor for TMD. To learn what causes may lie behind clenching and grinding, read our article on the causes of teeth grinding.
Connective tissue and joint mobility
Women tend to have more elastic connective tissue and greater joint mobility. What is an advantage elsewhere can mean less stability at the temporomandibular joint – the structures are more susceptible to improper loading.
Typical TMD symptoms in women at a glance
The symptoms of TMD are rarely limited to the jaw. Because the signs are so varied, they are often attributed to other causes. The following signs occur particularly frequently:
- Jaw and facial pain: A feeling of tension or pressure in the area of the temporomandibular joint, often on one side.
- Headaches: often in the temple and forehead area, frequently especially pronounced in the morning after waking. Migraine is a distinct headache disorder; however, an existing migraine can be intensified by TMD.
- Neck and shoulder tension: The chewing muscles are closely connected with the muscles of the throat and neck.
- Ringing in the ears and ear pain: tinnitus or a feeling of pressure in the ear without a detectable ear-related cause. A review article found ringing in the ears significantly more common in people with TMD than in people without TMD.
- Jaw popping or grating: Sounds when opening and closing the mouth.
- Restricted mouth opening: The feeling that the jaw “locks” or cannot be opened wide.
- Dizziness and sleep disturbances: are frequently reported by those affected; whether they stem from TMD must be clarified on a case-by-case basis.
If persistent pain occurs in the temporomandibular joint, that is a clear signal to have the cause professionally evaluated instead of treating the symptoms in isolation.
Why TMD is often recognized late in women
The wide range of symptoms means that many women first consult other medical fields – for headaches, muscle tension or ringing in the ears, for example. The connection with the temporomandibular joint is often overlooked. It is not unusual for months or years to pass before a temporomandibular disorder is identified as the common cause. A targeted, functional examination of the chewing system provides clarity here. We explain the role played by structured TMD diagnosis and treatment on our dedicated page.
How is TMD diagnosed?
It begins with a comprehensive medical history, in which symptoms, lifestyle factors, and possible triggers are recorded. With us, this process starts before your appointment: After booking your initial consultation, you will receive a link by text message or email to the digital medical history form “Nelly.” This is followed by a functional examination of the temporomandibular joints and the masticatory muscles. We palpate the muscles, measure mouth opening, listen for joint sounds, and use a brief screening test to determine whether a more detailed functional analysis is needed. Functional analysis is part of every treatment plan in our practice. If the findings indicate that a digital jaw joint measurement is necessary, we record the jaw movement three-dimensionally using the DMD system in a separate appointment. You can learn more about the possibilities of digital jaw joint measurement on our diagnostics page.
How TMD is treated
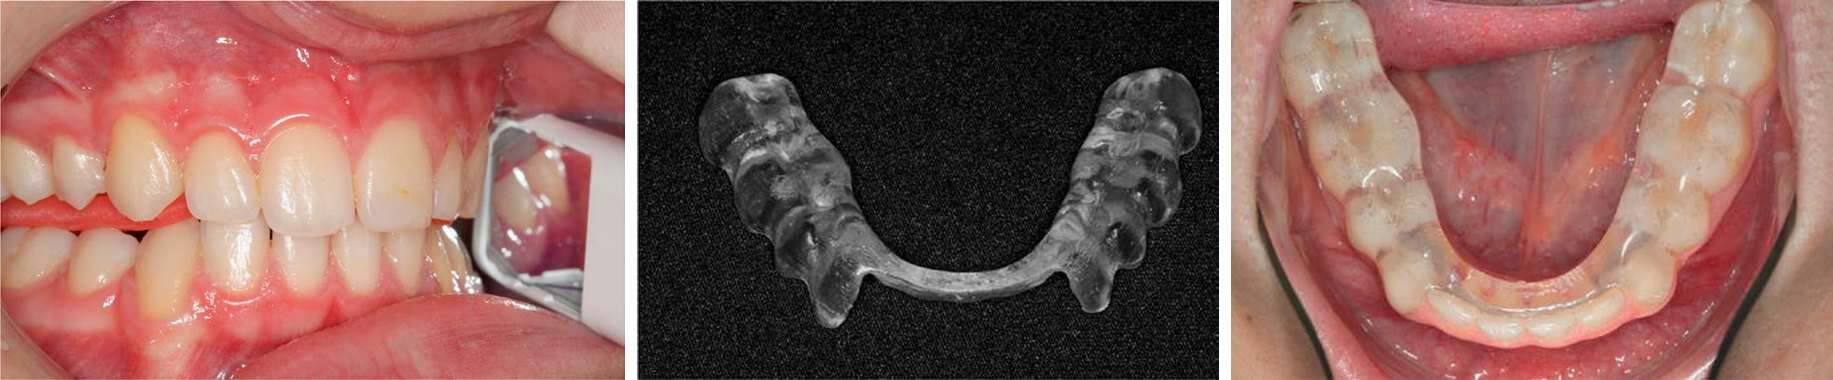
Treatment usually begins with a reversible approach: a custom-fabricated occlusal splint. It relieves the muscles and temporomandibular joints and helps to find a relaxed position for the lower jaw. We scan both dental arches, determine the jaw relation, and fabricate the splint in our own in-house laboratory using 3D printing.
Physical therapy is often added, especially when the neck and shoulders are also affected. Home exercises and learning to recognize daytime clenching are also part of the treatment. Only after symptoms have resolved and the bite is stable do we discuss whether orthodontic correction makes sense, for example with aligners. This sequence – splint first, then orthodontic correction if necessary – has been described by Dr. Steinmaier (née Funke) as co-author in several professional publications. The combination of splint therapy and subsequent aligner treatment for TMD was described as early as 2010 in our predecessor practice Schupp-Ortho (Schupp, Haubrich & Neumann 2010).
Connection with sleep and nighttime breathing
In some of those affected, there is a connection between nighttime grinding, a TMD and breathing disorders during sleep. If you wake up in the morning with jaw pain, headaches and the feeling that your sleep was not restful, you should keep this area in mind as well. You will find information on when nighttime breathing pauses and snoring require treatment in our section on snoring and sleep apnea.
When you should seek medical advice
Isolated, temporary tension is usually harmless. However, if symptoms persist for several weeks, recur regularly, or limit your daily activities, professional evaluation is advisable. The earlier the connections are recognized, the more specifically the strain on the masticatory system can be reduced.
A temporomandibular disorder can be treated successfully in many cases once the cause has been identified. For the consultation, it helps to prepare a few points:
Keep a record for two to four weeks, noting when jaw, head, or neck pain occurs and how severe it is. Also note your menstrual cycle days, pregnancy, or menopause, so we can identify any hormonal connection. Bring records from other physicians, such as ENT, orthopedics, or neurology, as well as a list of your medications. Whether you have statutory or private health insurance: diagnostics, consultation, and care are the same for all patients at our practice.
You’ll find us in Cologne-Rodenkirchen, Hauptstr. 50, phone 0221 93 53 020. Feel free to schedule an appointment for an evaluation.
Sources, studies & further reading
- Schupp, W., Haubrich, J., & Funke, J. (2020). Behandlung mit Okklusionsschienen und deren Herstellung im digitalen Workflow. Informationen aus Orthodontie & Kieferorthopädie, 52(3), 227–231. doi:10.1055/a-1200-5934 (J. Funke = Dr. Julia Steinmaier)
- Schiffman, E., Ohrbach, R., Truelove, E., et al. (2014). Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) for Clinical and Research Applications. Journal of Oral & Facial Pain and Headache, 28(1), 6–27. doi:10.11607/jop.1151
- Deutsche Gesellschaft für Funktionsdiagnostik und -therapie (DGFDT) & DGZMK. S3-Leitlinie: Diagnostik und Behandlung von Bruxismus. AWMF-Registernr. 083-027, Version 2.1 (Januar 2026). register.awmf.org
- Schupp, W., Haubrich, J., & Neumann, I. (2010). Invisalign treatment of patients with craniomandibular disorders. International Orthodontics, 8(3), 253–267. doi:10.1016/j.ortho.2010.07.010
- Bueno, C. H., Pereira, D. D., Pattussi, M. P., Grossi, P. K., & Grossi, M. L. (2018). Gender differences in temporomandibular disorders in adult populational studies: A systematic review and meta-analysis. Journal of Oral Rehabilitation, 45(9), 720–729. doi:10.1111/joor.12661
- Mottaghi, A., Menéndez-Díaz, I., Cobo, J. L., González-Serrano, J., & Cobo, T. (2019). Is there a higher prevalence of tinnitus in patients with temporomandibular disorders? A systematic review and meta-analysis. Journal of Oral Rehabilitation, 46(1), 76–86. doi:10.1111/joor.12706
- Leucuța, D. C., Anton, D., & Almășan, O. (2024). Estrogen Hormones’ Implications on the Physiopathology of Temporomandibular Dysfunction. Journal of Clinical Medicine, 13(15), 4406. doi:10.3390/jcm13154406
Frequently asked questions about TMD symptoms in women
Why does TMD occur more often in women than in men?
The reasons are thought to be an interplay of hormonal influences on the temporomandibular joint, connective tissue that tends to be more elastic, and greater strain from stress-related teeth grinding. A single trigger usually cannot be identified.
Can hormonal changes make TMD symptoms worse?
Yes. Hormonal fluctuations – during the menstrual cycle, in pregnancy or during menopause, for example – can affect both how much strain the temporomandibular joint (jaw joint) can tolerate and how pain is perceived. Symptoms are therefore often more pronounced in certain phases of life.
Which TMD symptoms are often overlooked?
Headaches, tension in the neck and shoulders and ringing in the ears in particular are often attributed to other causes. The connection with the temporomandibular joint then goes unrecognized for a long time.
When should I have TMD symptoms checked?
If symptoms last longer than a few weeks, recur regularly or affect you in everyday life, a functional examination of the masticatory (chewing) system is advisable.
How is TMD treated in women?
Treatment does not fundamentally differ from that in men. It usually begins with a custom-made occlusal splint, often supplemented by physiotherapy and exercises. Orthodontic correction is only considered once the symptoms have subsided.
Can I get a splint during pregnancy?
If you are pregnant, we do not take X-rays. If diagnostics require an X-ray, we will take it after delivery. Until then, we rely on the examination of the temporomandibular joint and chewing muscles and on the digital scan, both without radiation. A bite splint is also possible during pregnancy. Please let us know if you are pregnant; we will adjust the examination and treatment accordingly.
Reviewed by Dr. med. dent. Julia Steinmaier, specialist in orthodontics · Last reviewed on June 26, 2026
Related Posts
These blog posts might also interest you.
 Jun 17, 2026Teeth Grinding Causes: 7 Reasons and How to Identify Your OwnRead more →
 Jun 16, 2026One-Sided Jaw Pain: Causes, Classification, and When Evaluation Makes SenseRead more →
 Nov 25, 2025What Is Bruxism? When Teeth Are Under Pressure at NightRead more →
Your orthodontist in Cologne!
Schedule your no-obligation consultation at JUST KFO – Dr. Steinmaier & Kollegen in Cologne.
Book online 24/7 in a few clicks · free parking in our courtyard

