Even for children, early treatment can be planned with clear aligners. This article shows a case where this was implemented in-house using the practice's own software.
Early aligner treatment in mixed dentition with in-house planning.
Clear Aligners for Children Too — A Modern Early Treatment Approach
Clear aligners are often thought of as a treatment for adults. In reality, they can also be a comfortable alternative to fixed braces or removable plastic appliances in early treatment for children. The underlying professional publication from our practice demonstrates this with a real case and describes the technical background of aligner treatment in childhood. Below, we explain the key points in accessible terms.
Why Aligners for Children Too?
Aligners were initially popular mainly with adults because their success depends on good compliance – the trays only work if they are worn consistently. However, experience now shows that many children also do well with aligners. For children, this means: a removable, nearly invisible tray instead of brackets or a plastic plate. They remove the trays for eating and brushing; teeth and gums can be cleaned more thoroughly this way than around fixed brackets.1
Why no additional bite blocks were needed
With a crossbite, the dental arches often need to be temporarily “uncoupled” during correction so that the affected tooth can move past its opposing tooth. With fixed appliances or an active plate, this requires additional bite blocks on the molars. With aligners, the foil itself takes over this function: it also covers the chewing surfaces, and this layer thickness keeps the bite open by a small amount.2 In the case described, fixed bite blocks could therefore be avoided.
A Treatment Example
The Initial Situation
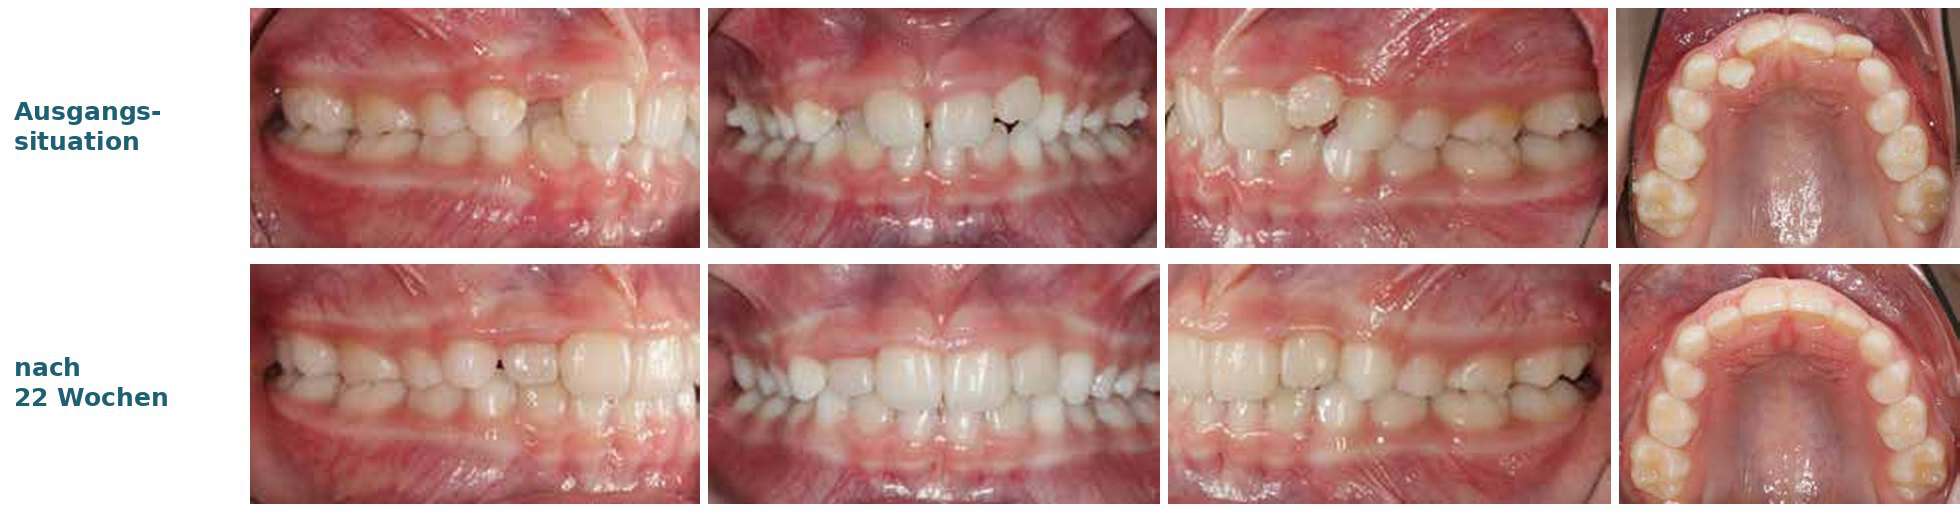
An eight-year-old girl presented at our practice. The upper right lateral incisor (tooth 12) was in crossbite with its lower opposing tooth (42), meaning it stood behind rather than in front of it. The upper jaw was too narrow, and the two upper first molars (16 and 26) were rotated forward. This indicated early treatment – a targeted correction while still in the mixed dentition. Alternatives included an active plate with an anterior spring or a so-called 2×4 mechanics (brackets on four incisors and two molars); both would have required temporary bite blocks in the posterior region. Together with the parents, the decision was made for aligners.
The treatment process
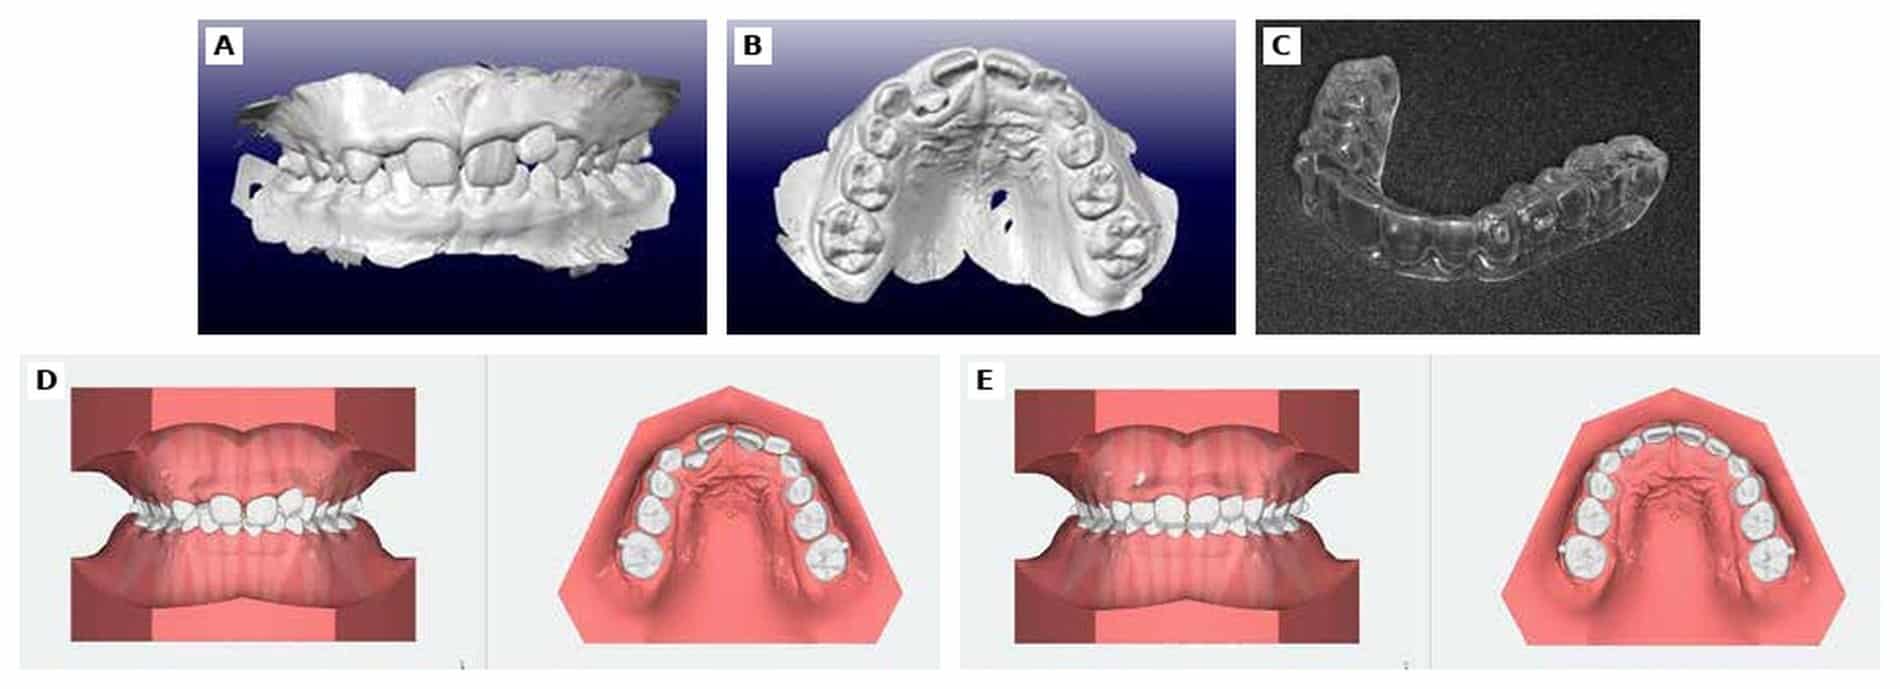
First, small tooth-colored retention elements (attachments) were bonded directly to the teeth: vertically on 16 and 26, and an additional one on the palatal side of tooth 12 so the aligner could push the tooth forward.3 Both jaws were then digitally captured with the intraoral scanner. In the planning software, we separated the teeth virtually and defined the target position.
Tooth 12 had the longest path: 4.4 millimeters outward. This distance was divided into eight equal steps of 0.55 millimeters each. For each step, a model was printed on the 3-D printer and the tray was thermoformed from PET-G foil (0.5 and 0.75 millimeters thick) – all in our own laboratory.4 The trays extend about 2 to 3 millimeters beyond the gum line so they hold well and transfer force effectively.6
The girl wore each tray for about one week, approximately 22 hours a day, and then switched independently to the next one. After 16 aligners, a refinement followed with six more (three planning steps with two trays each).
The Result
After 22 weeks and a total of 22 aligners, tooth 12 was positioned in front of its opposing tooth again. The front teeth were then in a functionally healthy relationship to each other. Fixed braces were not necessary. The upper jaw was also widened, and the rotated molars were straightened.
Which children are candidates for early aligner treatment
More important than age is the question of whether your child will wear the aligners almost all day and change them independently. In the case described, an eight-year-old managed this for 22 weeks. Not every misalignment in the mixed dentition can be corrected with aligners; sometimes a removable appliance or another device is a better fit. We clarify this after the examination in the initial consultation and show you the options side by side.
After booking the initial consultation appointment, you will receive the link to our digital medical history form “Nelly” by text or email; this way, you can answer the questions about your child’s medical history at home in peace.
After early treatment: A break usually follows until tooth eruption has progressed far enough. During this time, we see your child for follow-up appointments and check whether the result holds and whether a second treatment phase will be necessary later.
How much does aligner treatment cost for children?
Aligners are a private service; statutory health insurance does not cover them. For children and adolescents with KIG 3 to 5, the standard care with fixed braces remains the service covered by insurance. If the family chooses aligners instead, the treatment is a private service — the insurance does not contribute to it. You can pay the costs in interest-free installments for up to 18 months, directly through the practice. Whether you have statutory or private health insurance: diagnostics, consultation, and care are the same for all patients. More on our Costs & Insurance.
What this case demonstrates
Early aligner treatment can offer children a comfortable alternative to fixed appliances5 – provided the treatment is carefully planned and the child wears the aligners reliably. Learn more about treatment with clear aligners on our dedicated page, and more about child-friendly treatment in the Orthodontics for Children and Adolescents section. You can also read background information on crossbite in our article Recognizing and Treating Crossbite. A parent-friendly overview is provided in our article Can My Child Already Get Clear Aligners? To see how such treatment works in everyday life, visit our Case Example: Aligner Treatment in a Child.
Sources
- Abbate, G. M., Caria, M. P., Montanari, P., Mannu, C., Orrù, G., Caprioglio, A., & Levrini, L. (2015). Periodontal health in teenagers treated with removable aligners and fixed orthodontic appliances. Journal of Orofacial Orthopedics, 76(3), 240–250. doi:10.1007/s00056-015-0285-5
- Elkholy, F., & Lapatki, B. (2018). Recommendation of a novel film-thickness sequence, 0.4, 0.5 and 0.75 mm, for aligner systems. Journal of Aligner Orthodontics, 2(4), 295–304.
- Schupp, W., & Haubrich, J. (Hrsg.). (2015). Aligner Orthodontics. Quintessenz.
- Krey, K., et al. (2019). Complete digital in-office workflow for aligner treatment with a fused filament fabrication (FFF) 3D printer: Technical considerations and report of cases. Journal of Aligner Orthodontics, 3(3), 195–204.
- Azaripour, A., Weusmann, J., Mahmoodi, B., Peppas, D., Gerhold-Ay, A., Van Noorden, C. J. F., & Willershausen, B. (2015). Braces versus Invisalign®: Gingival parameters and patients’ satisfaction during treatment – a cross-sectional study. BMC Oral Health, 15, Artikel 69. doi:10.1186/s12903-015-0060-4
- Gao, L., & Wichelhaus, A. (2017). Forces and moments delivered by the PET-G aligner to a maxillary central incisor for palatal tipping and intrusion. The Angle Orthodontist, 87(4), 534–541. doi:10.2319/090216-666.1
Your orthodontist in Cologne!
Schedule your no-obligation consultation at JUST KFO – Dr. Steinmaier & Kollegen in Cologne.
Book online 24/7 in a few clicks · free parking in our courtyard
